What Is a Combined Acid base Disturbance?
A complex acid–base imbalance occurs when more than one process is altering acid-base balance at the same time. Instead of having a one straightforward picture, the blood reveals signs of two or more coexisting abnormalities. This situation is significant because a patient may look acidotic, alkalotic, or even close to normal on paper while still having a major underlying problem.
The most frequent combinations involve metabolic acidosis along with a different process such as respiratory alkalosis. In practice, this means one condition is lowering bicarbonate or adding to acid load, while another is driving down carbon dioxide through overbreathing. The result can be misleading unless you use a careful clinical approach and evaluate the full clinical picture.
A mixed acid base imbalance is not just a laboratory curiosity. It often signals a serious metabolic abnormality, ventilatory compensation that is too strong or insufficient, or an independent problem affecting the lungs and kidneys at the same time. Because of that, result review should always include serum chemistry, blood gas analysis, and the clinical context.
What Can an Elevated Anion Gap Signify?
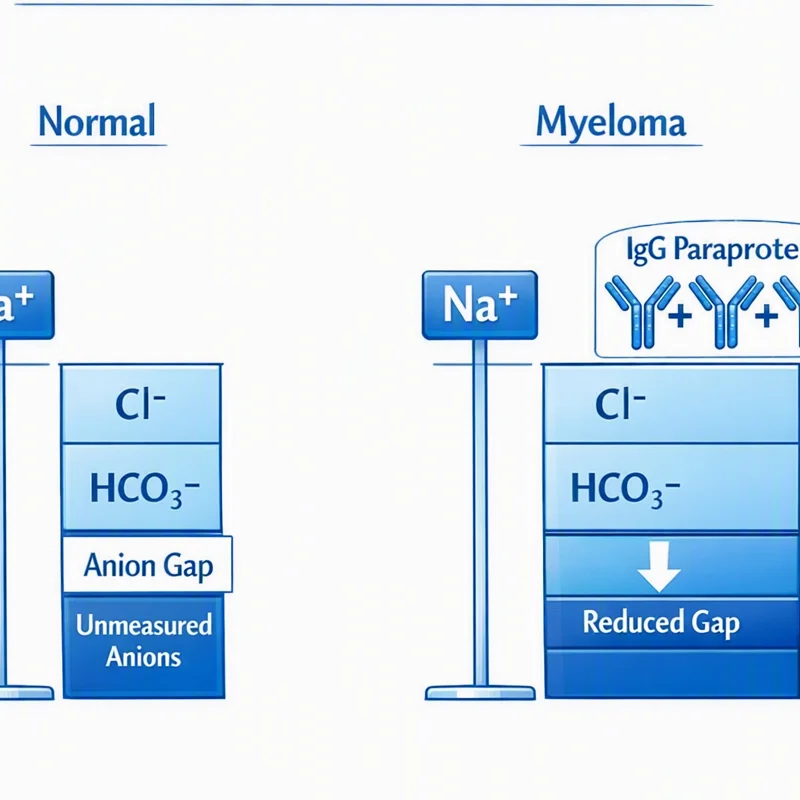
The anion gap is a derived value used to spot changes in electrolytes and acid-base status. It estimates the difference between measured cations and measured anions in the serum, and it offers a clue about the presence of unmeasured anions in the bloodstream. When the elevated anion gap is present, it usually suggests that extra acids are accumulating.
An increased anion gap is most closely linked to high anion gap metabolic acidosis. In this scenario, bicarbonate is depleted while acids build up, leaving behind negatively charged byproducts that are not directly measured on a standard panel. These may come from lactic acid, ketones, toxins, or impaired renal function.
Understanding the anion gap helps narrow the differential diagnosis. It does not tell you the exact cause by itself, but it clearly points to that the body is dealing with a specific type of acid loading or loss of acid excretion. That is why the anion gap is such a helpful part of laboratory interpretation.
How the Anion Gap Calculator Helps Interpretation
An Anion Gap Calculator simplifies the anion gap formula more straightforward to apply and helps reduce mistakes during rapid assessment. The calculation typically uses serum sodium, serum chloride, and serum bicarbonate. Because these values are often already available on a basic metabolic panel, the calculator turns raw serum chemistry into a more useful result.
The classic formula is: sodium minus the sum of chloride and bicarbonate. That calculated value is the anion gap. A higher number suggests the presence of extra unmeasured anions and may indicate a high anion gap metabolic acidosis. The calculator can also help you spot whether the pattern matches a single disorder or hints at a mixed acid-base disorder.
Using an Anion Gap Calculator is helpful because the result alone is not enough. You still need to compare it with the blood gas, the pH, the pCO2, and the patient’s symptoms. In other words, the calculator assists clinical reasoning, but it does not replace it. The best use is as part of a more complete diagnostic approach that includes compensation analysis and an underlying cause review.
Frequent Causes of Mixed Acid-Base Imbalances With Elevated Anion Gap
Several conditions can produce a combined acid-base disorder with an elevated anion gap. The most common are lactic acidosis, ketoacidosis, and renal failure. Each one can produce a elevated anion gap metabolic acidosis, and each one can also occur along with another disorder such as respiratory alkalosis or compensation from respiration that is more pronounced than expected.
Lactic acidosis develops when tissues are not getting enough oxygen or when cells cannot use oxygen normally. The outcome is increased lactate production and acid accumulation. It is often seen in critical illness, reduced perfusion, seizures, or major metabolic stress. If the patient is also ventilating rapidly, a respiratory alkalosis may occur simultaneously and make the pH less clearly abnormal.
Ketoacidosis happens when ketone production goes up, most often in poorly controlled diabetes, prolonged fasting, or metabolic stress related to alcohol. The ketoacids raise the anion gap and lower bicarbonate. If the person is ventilating quickly from pain, anxiety, infection, or sepsis, the blood gas may show a second disorder on top of the acidosis.
Renal failure can also lead to retention of acids that are normally cleared by the kidneys. As kidney function worsens, unaccounted acids accumulate and the serum anion gap may rise. This can happen gradually or acutely, and it often requires thorough review to patterns of electrolyte disturbance and the full serum chemistry profile.
Recognizing Mixed Disorders in Lab Results
The main step in recognizing a mixed acid-base disorder is not just observing an abnormal number. You need to read the arterial blood gas, including pH and pCO2, in combination with the chemistry panel. Together, these values indicate whether the body’s response is adequate or whether two separate processes are happening simultaneously.
You may see a low pH with low bicarbonate, which fits metabolic acidosis. But if the pCO2 is lower than expected, there may also be respiratory alkalosis. That is why the idea of a mixed disorder becomes important. The pH alone may not reveal the full story, especially if compensation is masking one component.
The delta gap is an additional helpful concept. It compares the rise in anion gap with the fall in bicarbonate. If the changes do not match expected patterns, a mixed process may be present. For example, a very high anion gap with only mild bicarbonate reduction may suggest an additional metabolic alkalosis. Likewise, an unexpectedly low pCO2 may point to superimposed respiratory alkalosis rather than simple compensation.
In practical terms, abnormal labs should raise questions like: Is the pH acidemic or alkalemic? Is the pCO2 moving in the direction you would expect? Does the anion gap fit the degree of bicarbonate loss? These checks help separate a straightforward pattern from a more complex metabolic disturbance.
Stepwise Process to Interpreting Outcomes
A clear process makes analysis much more straightforward. To begin, examine the pH to determine whether the patient is acidemic, alkalemic, or near normal. Afterward, determine whether the primary process seems metabolic or breathing-related. After that, assess the serum anion gap to see whether there is evidence of elevated anion gap metabolic acidosis. This stepwise method offers a reliable starting point for laboratory interpretation.
Next, use Winter's formula to calculate the expected respiratory compensation for metabolic acidosis. If the measured pCO2 is https://anion-gap-app106.rivetgarden.com/posts/what-can-cause-a-low-anion-gap-in-blood-tests well above than expected, there may be an additional respiratory acidosis. If the pCO2 is significantly lower than expected, respiratory alkalosis may be present. This remains one of the key steps in identifying a mixed acid-base disorder.
Finally, assess whether the observed pattern is physiologically consistent. True compensation is the body’s normal response to a primary disorder, but compensation has constraints. When the blood gas does not match the expected pattern, it implies more than one process. That is often the clue that the patient has an underlying cause requiring immediate attention.
A practical rule: if the anion gap is elevated and the pCO2 does not match the expected compensatory response, think past a single diagnosis and look for a second acid-base process.
Illustrations of Raised Anion Gap Mixed Disorders
A frequent case is an individual with sepsis who develops lactic acidosis. The infection drives poor tissue perfusion and lactate buildup, causing elevated anion gap metabolic acidosis. Simultaneously, the patient may hyperventilate from fever, pain, or systemic stress, producing respiratory alkalosis. The blood gas can show a pH that is not as low as expected because the two disorders partially offset each other.
Another example involves toxic alcohols. These substances can generate acids that raise the anion gap, leading to severe metabolic acidosis. If the patient is also breathing rapidly due to physiologic stress, agitation, or central nervous system effects, a mixed pattern may appear. The result is a high-risk clinical scenario that requires prompt recognition.
Salicylate poisoning is a classic mixed disorder. It often causes respiratory alkalosis early because the toxic exposure stimulates the respiratory center. Later, a high anion gap metabolic acidosis develops as acid metabolites accumulate. The combination can produce a deceptively near-normal pH, which is why blood gas analysis and serum chemistry must be reviewed together.
These examples show why laboratory interpretation matters. A patient can be severely ill even when one number seems only mildly abnormal. The anion gap formula, pH, pCO2, and clinical presentation all need to be interpreted together to identify the correct diagnosis.
When to Seek Urgent Medical Evaluation
Certain findings should warrant immediate clinical evaluation, particularly when they occur alongside an raised anion gap. Concerning lab values such as a extremely low bicarbonate, markedly abnormal pH, or severely elevated serum anion gap may indicate a life-threatening metabolic disturbance. These results need urgent clinical attention rather than routine follow-up.
Symptoms matter just as much as lab results. Changes in mental status, confusion, extreme weakness, rapid breathing, chest discomfort, or inability to stay awake can all signal a serious acid-base disorder. If the patient is not protecting the airway or cannot provide a reliable history, the urgency increases.
Shock is another significant warning sign. Poor perfusion can worsen lactic acidosis and rapidly destabilize the acid-base status. In that setting, the elevated anion gap may reflect a serious underlying cause such as sepsis, toxic ingestion, or organ failure. Urgent evaluation is needed because these conditions can progress quickly.
In short, a mixed acid-base disorder with a high anion gap is not something to ignore. It can represent a dangerous electrolyte disorder or systemic illness that needs prompt diagnosis and treatment.
Frequently Asked Questions
What is considered an elevated anion gap?
An elevated anion gap is a higher-than-expected result on an anion gap calculation using serum sodium, serum chloride, and serum bicarbonate. The exact cutoff can vary by laboratory because reference ranges differ, but a clearly increased value suggests excess unmeasured anions and raises concern for high anion gap metabolic acidosis. Always interpret the number with the rest of the blood gas and serum chemistry results.
How does a mixed acid-base disorder differ from a simple disorder?
A simple disorder has one primary acid-base problem with an appropriate compensatory response. A mixed acid-base disorder has multiple separate processes happening at the same time, such as metabolic acidosis plus respiratory alkalosis. The clue is often that the pH, pCO2, and bicarbonate do not fit the expected pattern for a single disorder.
Can a patient have both metabolic acidosis and respiratory alkalosis at the same time?
Certainly. This is a textbook combined acid-base disturbance. It can happen in sepsis, salicylate poisoning, liver disease, or other disorders where the body is making acid while also driving hyperventilation. In these cases, the pCO2 may be lower than expected for plain compensation, and the pH may appear less disturbed than the severity of illness would suggest.
What conditions most commonly cause a high anion gap?
Common causes include lactic acidosis, ketoacidosis, renal failure, toxic alcohols, and salicylate poisoning. These conditions all produce or hold onto acids that increase the anion gap. The best differential diagnosis comes from combining the anion gap with the arterial blood gas, clinical findings, and other laboratory interpretation clues.
How do you calculate and interpret the anion gap in lab results?
The anion gap formula uses serum sodium minus the sum of serum chloride and serum bicarbonate. Anion Gap Calculator can streamline that calculation and help prevent calculation mistakes. Once you have the result, compare it with the expected compensation using Winter's formula, review the pH and pCO2, and look for signs of a mixed disturbance. Interpretation works best when the calculated value is paired with the patient’s symptoms and underlying cause rather than interpreted alone.