What the Anion Gap Suggests in Iron Poisoning
The anion gap is a helpful way to understand an acid-base imbalance when a patient has a possible iron overdose. In toxicology, the anion gap helps clinicians identify whether metabolic acidosis is present and whether it may reflect significant systemic toxicity. Because iron poisoning can progress rapidly, the anion gap is often part of the early emergency assessment alongside the patient’s clinical presentation and serum electrolytes.
An anion gap calculator is not a diagnosis by itself, but it can help estimate whether the patient has a high anion gap metabolic acidosis, which may point to a dangerous metabolic derangement. In iron toxicity, this finding can raise concern about severe poisoning, especially when paired with vomiting, abdominal pain, hypotension, or altered mental status.
From a practical standpoint, the anion gap helps clinicians calculate and interpret the balance between measured cations and anions in the blood. When the gap rises, it often reflects unmeasured acids in the bloodstream. In the setting of iron poisoning, those acids may include lactate from poor tissue perfusion or other metabolites produced during severe toxicity.
It is important to remember that acid-base balance can shift quickly in iron overdose. Early on, a patient may have few laboratory abnormalities, but as toxicity worsens, the anion gap and other laboratory results may change. That is why the anion gap is best used as part of a more comprehensive diagnostic and risk stratification approach rather than as a standalone screening tool.
How to Calculate the Anion Gap
The typical anion gap formula relies on three basic laboratory values: serum sodium, serum chloride, and serum bicarbonate. The most common version is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
This is a simple calculation, but it can offer important clinical information in a suspected toxic ingestion. When using an anion gap calculator, the clinician inputs the serum sodium, serum chloride, and serum bicarbonate values obtained from the chemistry panel. The result can assist evaluate whether an acid-base disorder is present and whether further toxicology workup is needed.
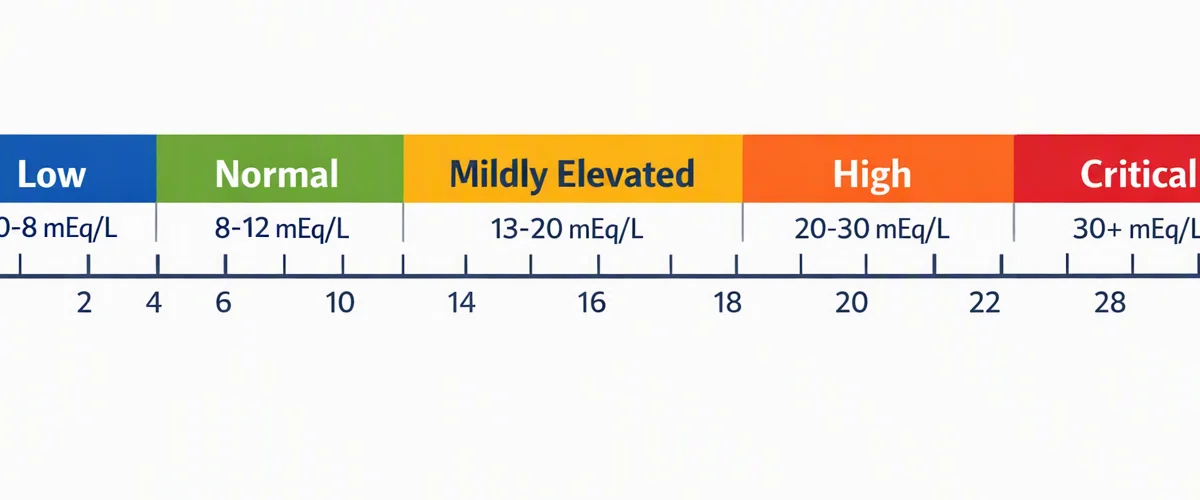
Normal ranges differ by laboratory, but a clearly elevated gap suggests increase of unmeasured anions. In iron overdose, that can point toward lactic acidosis or another severe metabolic disturbance. If the number is only mildly elevated, the result still needs clinical correlation because early iron poisoning can evolve over time.
Albumin also matters. Since albumin is a major unmeasured anion, low albumin can make the gap appear falsely normal or lower than expected. In that case, an albumin-corrected anion gap may be more informative. This correction is especially useful when the goal is to interpret laboratory results accurately in the context of emergency assessment and risk stratification.
For example, if a patient has low albumin, the measured anion gap may underestimate the severity of the acid-base disorder. Correcting for albumin helps avoid missing an early clue to significant iron toxicity. In practice, a calculator that includes albumin-corrected anion gap can improve diagnostic precision.
How Iron Toxicity May Increase the Anion Gap
Iron toxicity may increase the anion gap because severe poisoning disrupts cellular metabolism and tissue oxygen use. As iron levels climb, the body may develop lactic acidosis, one of the most important causes of increased anion gap metabolic acidosis in toxic ingestion. Lactate accumulates when cells cannot effectively use oxygen, and that excess acid increases the anion gap.
A key mechanism is cellular hypoperfusion. In substantial iron poisoning, fluid loss, shock, and cardiovascular instability can reduce blood flow to tissues. When perfusion declines, cells switch to anaerobic metabolism, generating more lactate. This process can rapidly worsen the acid-base disorder and raise the severity of systemic toxicity.
Another mechanism is oxidative injury. Free iron catalyzes harmful reactions that injure cells and mitochondria. This can disrupt energy production, impair organ function, and amplify metabolic derangement. The result may be increasing acidosis, rising lactate, and a higher anion gap.
In toxicology, the anion gap does not prove iron poisoning on its own, but it can support the clinical suspicion that the patient has a serious toxic ingestion. If the calculated gap is elevated and the clinical presentation fits, the clinician should evaluate for iron overdose immediately and monitor for progression. The combination of laboratory abnormalities and symptoms often drives urgency more strongly than any single number.
Key Signs and Healthcare Alert Signs
The patient picture of iron poisoning can progress in steps, and symptoms may appear before the full test picture is clear. First warning signs commonly include vomiting and abdominal pain. These symptoms are important because they can reflect direct gastrointestinal injury from iron tablets or liquid formulations.
As toxicity progresses, more serious signs may develop. Hypotension is concerning because it can indicate shock and poor tissue perfusion, both of which can worsen lactic acidosis and raise the anion gap. Persistent low blood pressure should never be dismissed when iron overdose is suspected.
Altered mental status is another critical red flag. Mental confusion, lethargy, agitation, or decreased responsiveness may signal severe systemic toxicity, inadequate perfusion, or worsening metabolic acidosis. When neurologic changes occur, the patient needs urgent reassessment and often escalation to emergency care.
Other symptoms may include diarrhea, dehydration, tachycardia, and signs of worsening illness. However, vomiting, abdominal pain, hypotension, and altered mental status are particularly important because they suggest a higher risk of complications. In an evidence-based approach, these clinical https://anion-gap-formula837.trexgame.net/can-low-albumin-lead-to-a-low-anion-gap findings should be reviewed alongside laboratory results to guide management and monitoring.
Because iron poisoning can be deceptive early on, a normal appearance does not always mean the ingestion is harmless. The symptom pattern, the estimated dose, and the timing of the toxic ingestion all matter. An anion gap calculator can assist with screening, but it should not replace bedside judgment when there is concern for serious poisoning.
Key Tests to Evaluate With the Anion Gap
Using an anion gap calculator in iron poisoning, the clinician should evaluate the anion gap together with several other labs. The primary iron-related measure is the serum iron level. This value helps assess the degree of exposure and supports toxicology assessment, especially when drawn at the appropriate time after ingestion.
Ferritin may also be ordered, although it is less helpful for acute severity than serum iron. Still, ferritin can offer additional information when evaluating iron status and interpreting laboratory results. Another helpful marker is transferrin saturation, which can reflect how fully transferrin binding capacity has been exceeded by excess iron.
An arterial blood gas is useful because it helps assess pH, bicarbonate status, and respiratory compensation. In a patient with possible iron toxicity, the arterial blood gas can show whether the patient truly has metabolic acidosis and whether there is a mixed acid-base disorder. This is especially critical when the chemistry panel and the clinical presentation do not align exactly.
Lactate should also be checked because it often rises in significant iron poisoning. Elevated lactate supports the possibility of lactic acidosis from cellular hypoperfusion or mitochondrial dysfunction. When lactate is high and the anion gap is elevated, the combination strengthens concern for serious systemic toxicity.
Beyond these tests, clinicians often check serum electrolytes, kidney function, glucose, and liver tests as part of the overall diagnostic picture. The goal is to judge severity, monitor for complications, and identify whether the patient needs aggressive treatment. In practice, the anion gap is one piece of a more comprehensive toxicology assessment.
Drawbacks of the Anion Gap in Iron Overdose
Although the anion gap is valuable, it has significant limitations. A normal anion gap does not automatically show the patient is safe. In the first stages of iron poisoning, the gap may still be normal before acidosis develops. In other cases, the patient may have a mixed acid-base disorder that masks the true severity of the metabolic problem.
As an example, vomiting can produce metabolic alkalosis, which may somewhat counteract metabolic acidosis on paper. This means the calculated anion gap may appear less striking than the clinical picture suggests. That is why clinical correlation is vital. Laboratory results should always be interpreted in the context of symptoms, timing, and the suspected toxic ingestion.
Albumin also affects interpretation. If albumin is low, the measured anion gap may be misleading. An albumin correction or albumin-corrected anion gap can uncover hidden high anion gap metabolic acidosis. This is especially relevant in ill patients, where low albumin is common and the risk of downplaying metabolic derangement is higher.
A further limitation is that the anion gap does not identify the exact cause of acidosis. It can suggest a problem, but it cannot distinguish iron toxicity from other causes of lactic acidosis or intoxication by itself. That is why toxicology decisions should integrate the anion gap with serum iron level, arterial blood gas, lactate, ferritin, transferrin saturation, and bedside findings.
In short, the anion gap is a diagnostic aid, not a definitive answer. It is strongest when used for following trends over time, helping clinicians evaluate whether treatment is working or whether the patient is deteriorating.
When iron overdose Requires emergency treatment
Every suspected iron toxicity that has symptoms or unusual lab findings should be treated as an emergency. If the patient has nausea and vomiting, abdominal pain, hypotension, altered mental status, or evidence of metabolic acidosis, rapid escalation is warranted. In these situations, the most prudent next step is to contact the poison center for immediate guidance and to arrange evaluation in the ER.
Urgent care is especially important crucial when the anion gap is elevated, lactate is rising, or the arterial blood gas shows worsening acidosis. Such results can signal severe iron poisoning and a greater risk of adverse outcomes. Rapid recognition matters because timely treatment can affect outcomes.
Supportive care is the foundation of emergency management. This may include IV fluids, correction of shock, tracking vital signs, and ongoing lab evaluation. When the case shows significant toxicity, chelation therapy may be started, often with deferoxamine as the treatment used for iron poisoning.
Deferoxamine binds free iron and may help reduce ongoing injury. The decision to use it depends on the clinical severity, symptoms, test findings, and expert toxicology input. Since treatment thresholds may differ based on the case, poison control involvement is extremely useful for evidence-based recommendations and risk assessment.
Do not hesitate for symptoms to worsen if iron poisoning is suspected and the patient is unwell. Serious poisoning may advance rapidly, and the exact phrase "Anion Gap Calculator" the anion gap may rise as the patient’s condition deteriorates. Immediate urgent assessment gives the best opportunity to evaluate the extent of the overdose, monitor for complications, and start appropriate treatment promptly.
FAQ on Anion Gap & Iron Overdose
In what way does anion gap aid assess iron overdose?
The anion gap assists spot whether a patient with likely iron overdose has an acid-base disorder, especially high anion gap metabolic acidosis. In toxicology, that can raise concern for significant iron poisoning and lead to closer monitoring, additional laboratory results, and urgent clinical evaluation.
Can iron overdose result in a high anion gap metabolic acidosis?
Absolutely. Iron toxicity can cause lactic acidosis through cellular hypoperfusion, shock, and oxidative injury. As lactate builds up, the anion gap can climb, leading to high anion gap metabolic acidosis. This finding often suggests more severe systemic toxicity.
What lab values should be checked with an anion gap calculator?
At minimum, the calculator uses serum sodium, serum chloride, and serum bicarbonate. In suspected iron poisoning, clinicians should also check albumin, albumin-corrected anion gap, arterial blood gas, lactate, serum iron level, ferritin, and transferrin saturation to better evaluate severity.
Can a normal anion gap eliminate iron poisoning?
No. A normal anion gap does not rule out iron poisoning. The patient may be early in the course, or there may be a mixed acid-base disorder or low albumin affecting interpretation. Clinical correlation and toxicology assessment remain essential.
At what point should someone with suspected iron overdose seek emergency care?
Emergency care is needed right away if there is vomiting, abdominal pain, hypotension, altered mental status, or any concern for worsening metabolic acidosis. Poison control should be contacted promptly, and the patient should be evaluated in the emergency department for possible supportive care and chelation therapy with deferoxamine if indicated.